Home › Toenail Fungus in Children
Toenail Fungus in Children: Symptoms, Treatment, and When to See a Doctor
By Best Toenail Fungus Treatments · Reviewed 15 Nov 2026 · 11 min read

Home › Toenail Fungus in Children
By Best Toenail Fungus Treatments · Reviewed 15 Nov 2026 · 11 min read
If you think your child has toenail fungus, see a pediatrician or pediatric dermatologist before starting any treatment.
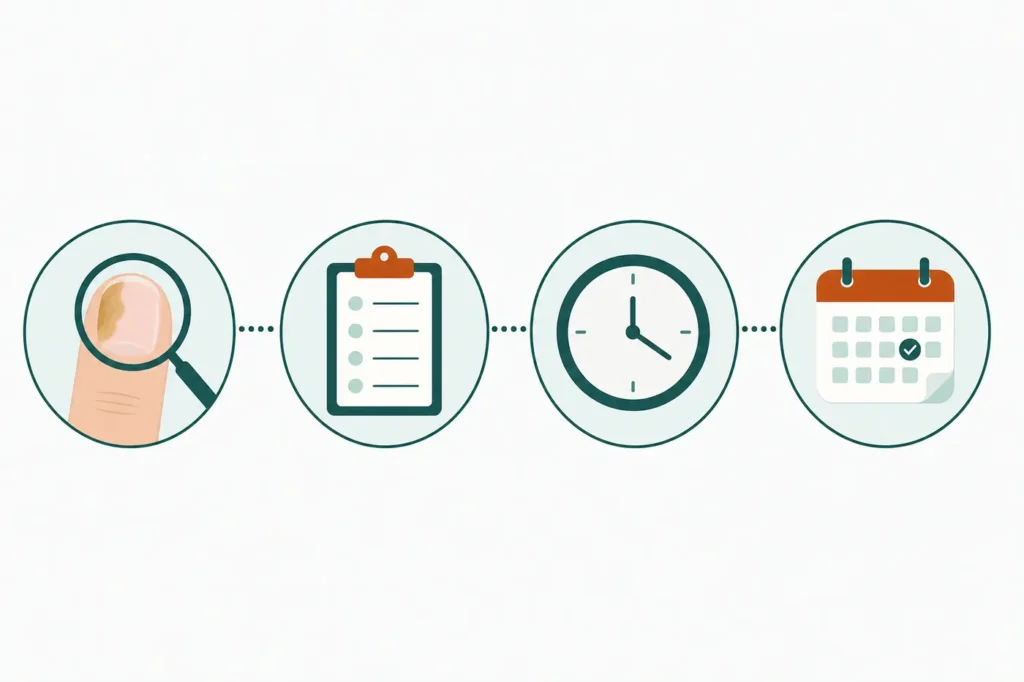
What a pediatrician typically does
| Step 1 | Step 2 | Step 3 | 3–6 mo |
|---|---|---|---|
| Confirm with KOH, culture or PAS stain | Assess severity and nails involved | Watch mild cases or start doctor-supervised treatment | Follow-up to check response |
Doctor-supervised treatment in children may be ciclopirox lacquer or a supervised course of oral prescription medicine; a pediatrician or dermatologist decides.
Key Facts
Prevalence
0.16–0.44% of children (vs 3–12% adults)
How it’s diagnosed
KOH scraping or fungal culture
See a doctor if
Any nail change, before any treatment
First-line Rx
Off-label; weight-based, pediatrician-supervised
Toenail fungus is significantly less common in children than in adults. A Canadian survey of 2,500 children found a prevalence of 0.16–0.44%, compared to 3–12% in the general adult population (Gupta AK et al., J Am Acad Dermatol 1997; AAFP 2015).
Several factors account for this difference:
Important differential: Nail changes in children are frequently caused by trauma from footwear or sports, nail biting, ingrown nails, or eczema — conditions that look like fungal infection but require different treatment. Lab testing is essential before diagnosing onychomycosis in a child.
When onychomycosis does occur in children, symptoms are similar to adults:
See early-stage toenail fungus signs →
These same signs can be caused by trauma, psoriasis, or other skin conditions. A pediatrician will typically order a KOH scraping or culture before treating.
Antifungal drug use in children for nail fungus is off-label for most approved medications:
Never give a child adult doses of antifungal medications. Always consult a pediatrician or pediatric dermatologist.
No. Toenail fungus is much less common in children than adults. One Canadian survey found 0.16–0.44% of children affected, compared to 3–12% in adults (Gupta AK et al., JAAD 1997; AAFP 2015). Nail changes in children are more often caused by trauma, skin conditions, or nail biting than by fungal infection.
Terbinafine is FDA-approved for tinea capitis (scalp ringworm) in children aged 4 and older, but it is not FDA-approved for onychomycosis (nail fungus) in children. Pediatric use for nail fungus is off-label and must be supervised by a pediatrician or dermatologist. Dosing is weight-based (Gupta AK & Paquet M, Pediatr Dermatol 2013). Never give a child adult doses.
OTC antifungal products (undecylenic acid, tolnaftate) are generally formulated for adults. Most OTC nail products carry age restrictions (typically “do not use on children under 12” or similar). Always read the label. More importantly, confirm the diagnosis before treating — nail changes in children are often not fungal. Consult a pediatrician first.
Yes. Fungal infections are contagious and can spread through direct contact or shared items (towels, socks, nail clippers). If one child in the household has onychomycosis, other family members should be checked. Treat infected family members, and avoid sharing personal foot hygiene items until the infection is resolved.
Medical disclaimer: This page is informational only and not medical advice. Consult a licensed pediatrician or pediatric dermatologist for diagnosis and treatment of nail conditions in children.
Sources: Gupta AK, Sibbald RG, Lynde CW, et al. J Am Acad Dermatol 1997;36(3 Pt 1):395–402 (pediatric onychomycosis prevalence); Gupta AK, Paquet M. Systemic antifungals to treat onychomycosis in children: a systematic review. Pediatr Dermatol 2013;30(3):294–302; Lamisil FDA prescribing information (terbinafine granules, tinea capitis ages 4+, nail not approved for pediatrics); AAFP 2015 (adult prevalence 3–12%); Elewski BE. Clin Microbiol Rev 1998;11(3):415–429 (onychomycosis overview).
Start with a pediatrician visit to confirm the diagnosis before any treatment.